E-Max Veneers: Treatment Guide
E-max veneers are thin lithium-disilicate ceramic coverings bonded to the front of teeth. They are used to improve colour, shape, small gaps, worn edges and mild alignment problems while preserving more tooth structure than a full crown when the case is suitable.
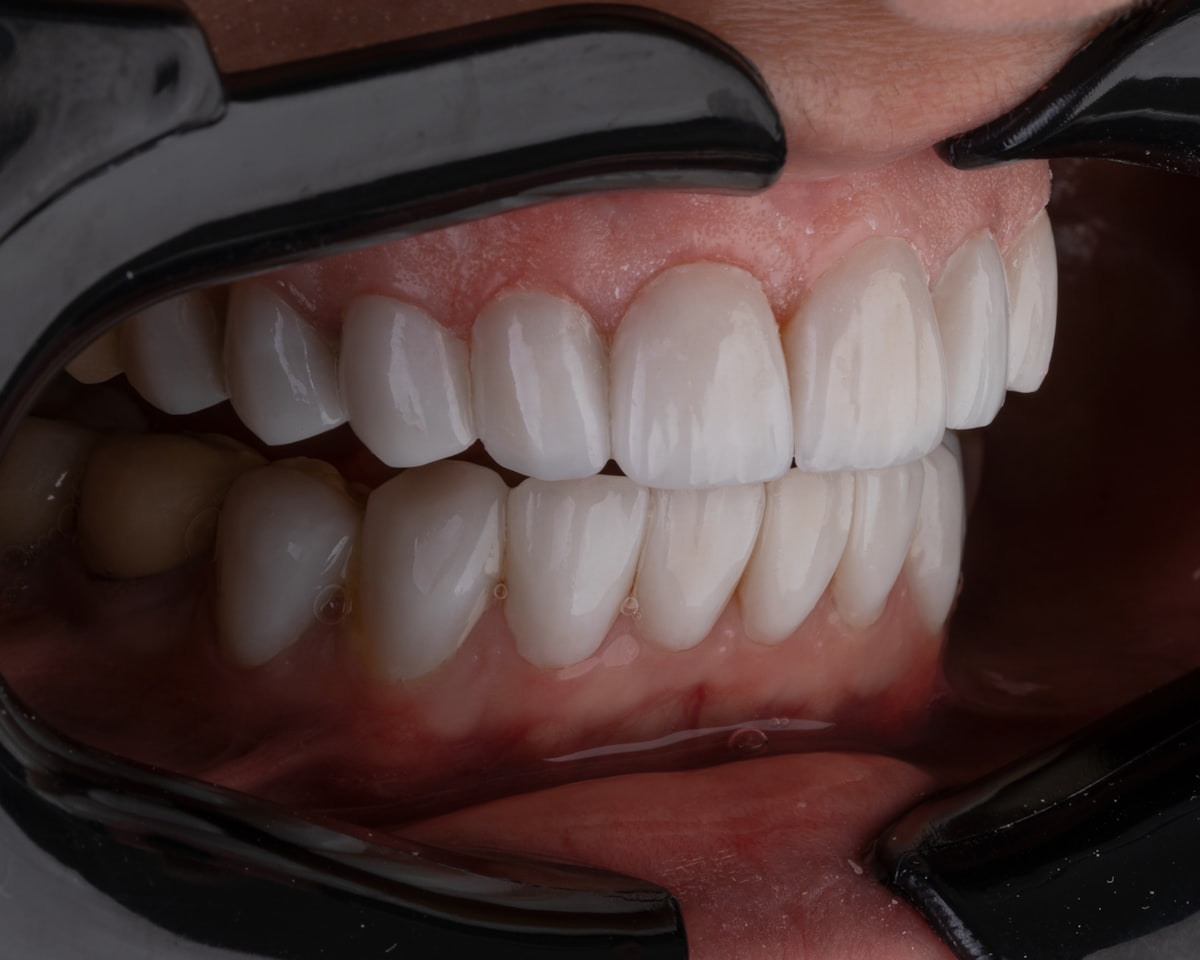
What is e-max veneers?
E-max is a widely used lithium-disilicate ceramic valued for translucency, strength and its ability to bond to enamel. An E-max veneer covers mainly the front surface and edge of a tooth. It is different from a crown, which surrounds most or all of the visible tooth. The indication must be based on remaining enamel, bite and the amount of colour or shape change required.
A safe plan explains the diagnosis, why the method is appropriate, what alternatives exist and what may change after examination. For international patients, an online quote is preliminary until the treating dentist examines the mouth and reviews the required imaging. Dentist Guide Network provides independent comparison guidance; final diagnosis and consent remain with the treating professional.
Who is a good candidate?
Good candidates often have healthy gums, sufficient enamel, stable bite and cosmetic concerns such as intrinsic staining, small spaces, uneven shapes, mild rotations or worn incisal edges. Veneers may also replace older composite work. Patients with severe crowding, active decay, significant gum disease or uncontrolled bruxism may need alternative or preliminary treatment.
Veneers are irreversible because some enamel is usually prepared. They cannot correct every position or bite problem, and very dark teeth may require more opaque ceramics or another treatment. Extremely thin ‘no-prep’ veneers can look bulky when added to teeth that are already prominent.
Suitability should include medical history, medicines, allergies, nicotine use, previous treatment, gum health, bite forces and the patient’s ability to maintain the result. Photographs support triage, but X-rays or CBCT may still be required.
What are the main benefits?
- High translucency can imitate natural enamel.
- Adhesive bonding to enamel provides a conservative restorative option.
- Resists staining better than direct composite.
- Allows precise control of shape, edge position and small spaces.
- Can be digitally designed and tried in before final bonding.
The strongest outcome is not simply the whitest or fastest result. It is a result that preserves appropriate tissue, functions comfortably, can be cleaned and has a realistic maintenance pathway.
How does the procedure work?
- Consultation and diagnosis: the dentist evaluates enamel, gums, bite, photographs, X-rays and the patient’s aesthetic goals.
- Smile design: proposed length, width, midline and shade are planned digitally or through a wax-up.
- Mock-up: a temporary preview may be placed without drilling so the patient can assess shape and speech.
- Preparation and scanning: a controlled amount of enamel is prepared and a digital or conventional impression is recorded.
- Laboratory fabrication and try-in: each veneer is made individually and evaluated for fit, colour and proportion.
- Bonding: the tooth and ceramic are conditioned, adhesive resin is applied and the bite is carefully refined.
The sequence may change after examination. Gum disease may need stabilisation, infection may need imaging, or temporary work may need to remain longer. International patients should keep enough travel flexibility for checks and adjustments.
Materials, techniques and digital dentistry
Veneers may be pressed or milled, monochromatic or layered, and prepared with minimal, conventional or no-prep designs. The ceramic thickness and translucency should match the underlying tooth colour. In some smiles, whitening the untreated teeth before selecting the final shade produces a more consistent result.
Digital scans, photographic records, guided planning and computer-aided manufacturing can improve communication and reproducibility. They do not replace clinical judgement. Patients should ask which stages are digital, who makes the restoration and how fit, aesthetics and bite are verified.
How long should an international patient stay?
The typical pathway is commonly 5–7 days for assessment, preparation, try-in and bonding. Stay length should reflect the number of stages, laboratory production, try-ins and post-treatment review. Same-day techniques are useful in selected cases, but speed should not remove necessary diagnostic, healing or verification steps.
Recovery and aftercare
Most patients return to normal activity quickly. Mild sensitivity to cold or pressure can occur after preparation and bonding. The gums may feel tender for a few days. Daily brushing, interdental cleaning and avoiding habits such as nail biting, ice chewing and opening packaging with the teeth help protect the margins.
Written instructions should explain diet, cleaning, medicines, normal symptoms, warning signs and who to contact. Long-term maintenance normally includes daily plaque control, professional examinations and management of grinding or smoking. Guarantee conditions should be supplied before payment.
Risks, limitations and possible complications
Risks include sensitivity, edge fracture, debonding, gum inflammation, colour mismatch, visible margins and the future need for replacement. Bonding is strongest when much of the preparation remains in enamel. Bruxism and deep bites increase mechanical demand and may require orthodontics, bite adjustment or a night guard.
No responsible page should promise risk-free treatment, no discomfort for every patient or automatic lifetime survival. Consent should cover common risks, important uncommon risks and the plan if a problem occurs after the patient returns home.
Prefer to fill in a quick form?
Fill in our short consultation form and our patient team will prepare your personalised offer.
How does it compare with alternatives?
Compared with composite veneers, E-max generally offers better stain resistance and long-term surface gloss but costs more and usually requires laboratory stages. Compared with zirconia crowns, veneers preserve more tooth structure but cannot adequately protect a severely weakened tooth. The correct choice is based on tooth condition, not solely aesthetics.
Compare options by tissue preservation, need for surgery, treatment time, hygiene, repairability and future maintenance, not only the initial package price.
Questions to ask before booking
- Who is the treating dentist, and what is their relevant experience?
- What diagnosis supports every item in the plan?
- Is there a more conservative or non-surgical alternative?
- Which brand and material will be documented?
- What may change after examination?
- How many appointments and try-ins are included?
- Who manages complications after I return home?
Editorial and clinical quality check
Before publication, replace generic claims with verifiable details from the actual provider network. Add the name and credentials of the clinical reviewer, the review date, original photographs or diagrams, and a clearly labelled explanation of how Dentist Guide Network evaluates clinics. Any price, guarantee, treatment duration or success statement should match the written terms offered to the patient. Avoid superlatives that cannot be substantiated. This page should be reviewed whenever materials, prices, clinical partners or travel arrangements change.
Frequently asked questions about e-max veneers
Key takeaway
E-max veneers are thin lithium-disilicate ceramic coverings bonded to the front of teeth. They are used to improve colour, shape, small gaps, worn edges and mild alignment problems while preserving more tooth structure than a full crown when the case is suitable. The correct plan is individual. Use online information to prepare questions, then rely on examination and appropriate imaging for the final clinical decision.
Read further before you decide
If you want the clinical detail behind veneers rather than the commercial summary:
- E max veneers
- Porcelain veneers
- Veneer aftercare
- Failed veneers
Related reading
Medical sources used for this page
- American Dental Association, MouthHealthy: Veneers
- NHS: Dental treatments
- American Dental Association, MouthHealthy: Crowns